You are 19. You noticed more hair on the pillow, then more in the bathroom drain. Then a friend made a comment about your forehead. You went home, took a photo under the tube light, and it looked worse than you thought.
Now you are searching for a hair transplant.
Stop for ten minutes and read this first. Not because a transplant is bad — it is an excellent, permanent procedure when it is done for the right person at the right time. But at 18 to 22, most men who want one should not get one yet. Not because of cost. Because of biology.

You are 19. You noticed more hair on the pillow, then more in the bathroom drain. Then a friend made a comment about your forehead. You went home, took a photo under the tube light, and it looked worse than you thought.
Now you are searching for a hair transplant.
Stop for ten minutes and read this first. Not because a transplant is bad — it is an excellent, permanent procedure when it is done for the right person at the right time. But at 18 to 22, most men who want one should not get one yet. Not because of cost. Because of biology.
This article explains exactly how a hair transplant surgeon decides between medication and surgery at this age, what happens if you get the sequence wrong, and the small number of cases where surgery before 25 is genuinely the right call.
Why hair loss hits differently at this age
At 35, hair loss is disappointing. At 19, it can feel like it is rewriting who you are — right at the point in life when college photos, first jobs, and first relationships are happening.
That urgency is real, and no doctor should dismiss it. But urgency is also exactly what pushes young men into decisions they regret at 30. The single most common regret we see is not “I waited too long.” It is “I had surgery too early.”
What is actually happening to your hair
Male pattern hair loss — androgenetic alopecia — is genetic and hormone-driven. Testosterone converts into DHT (dihydrotestosterone). In men who are genetically sensitive to it, DHT binds to receptors on hair follicles at the hairline, temples, and crown.
Those follicles do not die overnight. They miniaturise. Each growth cycle produces a slightly thinner, shorter, lighter hair, until eventually the follicle produces nothing visible at all.
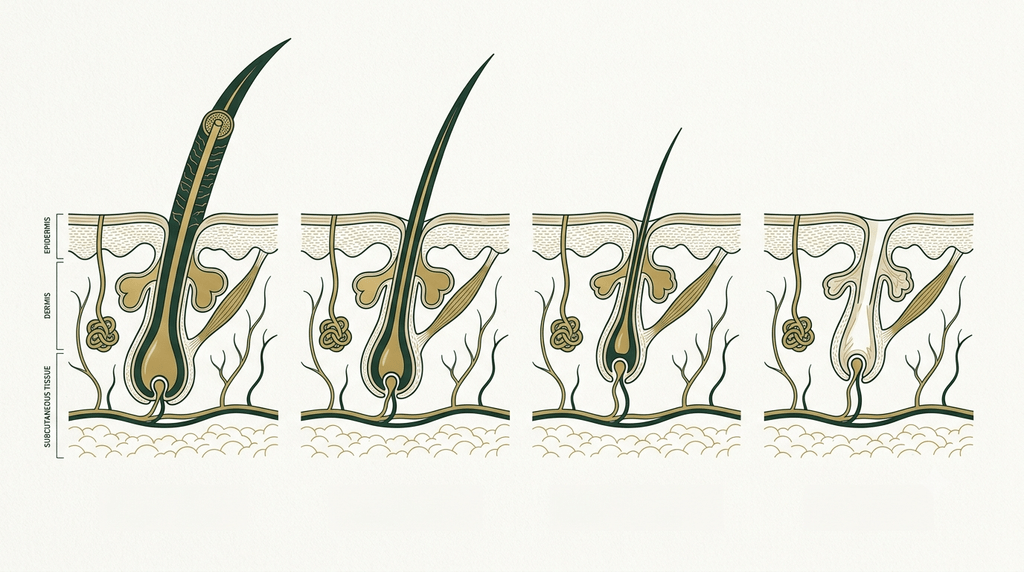
This matters enormously for your decision, and here is why: miniaturising hair is still alive. Medication can rescue it. Dead follicles cannot be rescued by anything except transplantation.
So the real question at 18–22 is not “medication or surgery.” It is: how much of your hair is still rescuable, and has your pattern finished revealing itself?
The fact that changes everything: your pattern is not finished
If you start losing hair at 18, you are not going to stop losing hair at 22. Androgenetic alopecia is progressive. It continues for decades.

Someone who is a Norwood 2 at 19 may be a Norwood 5 at 32. Nobody — no surgeon, no scan, no AI app — can tell you with certainty which one you will be. Family history gives a hint, not a guarantee.
This creates the central problem with early surgery.
Why a transplant at 19 can look wrong at 29
A hair transplant moves DHT-resistant hair from the back and sides of your head to the thinning areas. That transplanted hair is permanent — it keeps its resistance and grows for life.
But it does not protect the hair around it.
Picture this sequence. At 19, you have a transplant to rebuild a low, straight, teenage hairline. It looks excellent for three years. Meanwhile, the native hair behind that hairline keeps miniaturising, because nothing stopped the underlying process. By 27, you have a dense transplanted strip in front and thinning behind it. By 31, that strip is an island of hair floating on a bald scalp — one of the most recognisable signatures of a transplant done too early.

Now you need a second surgery to fix it. Except your donor area is a finite resource. You already spent a large chunk of it building a hairline that no longer suits your face or your degree of loss. You cannot make more donor hair. This is the trap.
A surgeon planning for a 19-year-old is not planning for age 22. They are planning for age 50, with a donor supply that has to last that long.
When medication is the right first choice — which is most of the time
For the large majority of men aged 18 to 22, the correct plan is medical treatment first, consistently, for at least 12 months, with proper documentation of what happens.
Medication does two things surgery cannot. It slows or stops further loss, and it can thicken hair that is miniaturised but still alive. Surgery does neither.
Topical minoxidil
Minoxidil is applied to the scalp and works by extending the growth phase of the hair cycle and improving blood supply to the follicle. It is available without prescription, but strength and formulation (solution versus foam) should still be chosen with a doctor, because scalp irritation and application technique affect whether it works.

Two things people get wrong: they stop at three months because “nothing happened,” and they panic at the early shedding phase. A temporary increase in shedding in the first 4–8 weeks is normal and is a sign of hair cycles resetting — not a sign the drug is destroying your hair.
Oral finasteride
Finasteride blocks the enzyme that converts testosterone to DHT, addressing the actual cause rather than the symptom. It is prescription-only, approved for men aged 18 and above, and it is the single most effective medical treatment available for male pattern hair loss.
It also requires an honest conversation, which some clinics skip. A small percentage of men in clinical trials reported sexual side effects such as reduced libido or erectile difficulty. In most cases these resolve after stopping. There is ongoing debate about persistent symptoms in a small subset of users. The drug must not be handled by women who are pregnant or may become pregnant.
None of this means you should avoid it. It means the decision belongs to you and your doctor after a proper discussion, not to a forum thread or a YouTube comment. Dose, duration, and monitoring are all medical decisions.
Supporting treatments
These are genuinely useful alongside the two core drugs, and genuinely useless instead of them:
- Ketoconazole-based medicated shampoo — helps with scalp inflammation and seborrhoeic dermatitis, which worsen shedding
- GFC (growth factor concentrate) — also made from your own blood, but the platelets are activated and the growth factors separated out, so what is injected is the growth factor payload without the red and white cells. It tends to show visible improvement faster than PRP and causes less post-injection scalp irritation. The trade-off is cost and evidence: GFC is newer, most published work is small-scale, and long-term data is thinner than for PRP. Like PRP, it stimulates follicles that are still alive — it cannot regrow hair where the follicle is gone.
- Correcting deficiencies — iron, vitamin D, thyroid problems and protein deficiency all cause or worsen shedding, and all are common in young Indian men with irregular hostel or PG food. These need a blood test, not a guess.
A note on what does not work: onion juice, coconut oil head massage for regrowth, castor oil, “herbal DHT blocker” capsules bought online, and biotin supplements taken without a proven deficiency. Oil and massage improve scalp comfort and reduce breakage. They do not affect DHT, and they will not regrow a receding hairline.
What a realistic first year looks like
| Timeline | What to expect |
|---|---|
| Month 0–1 | Baseline photos taken under standard lighting, blood tests done, treatment started |
| Month 1–2 | Possible temporary shedding phase — this is expected, not failure |
| Month 3–4 | Shedding slows or stops; no visible regrowth yet |
| Month 6 | First measurable change; comparison photos start to show thickening |
| Month 9–12 | Peak visible improvement in density; pattern stability can now be assessed |
At month 12, you and your doctor look at the photo comparison and answer one question: has the loss stopped? That answer determines everything that comes next.
When a transplant before 25 genuinely makes sense
It would be dishonest to say “never.” There are clear situations where early surgery is correct:

1. Scarring from injury, burns or surgery. A scar from an accident, a burn, or a previous operation is not progressive hair loss. It is a fixed defect. There is nothing to wait for, and medication will not help. Transplantation is the correct treatment at any age.
2. Eyebrow, beard or moustache restoration. These areas are not subject to the progressive pattern that affects the scalp, so the “wait and see” logic does not apply in the same way.
3. Documented stability on medication for two or more years. A man who started medication at 19, has photographic evidence of no further loss at 22, has limited and clearly defined recession, and a strong donor area, is a legitimate candidate for a conservative procedure.
4. Very limited, stable recession with a strong family history of mild loss. If the men in your family stop at a mature hairline and never progress further, the risk calculation is different. This needs genuine assessment, not wishful thinking — most men overestimate how mild their family history is.
Notice what every one of these has in common: there is evidence, not hope. The default at this age is to wait and treat. Surgery is the exception that has to be justified.
Even in these cases, a good surgeon will design conservatively — a mature hairline placed slightly higher than you want, with the density concentrated where it frames the face, deliberately preserving donor hair for the future. If a clinic offers you the low, flat, teenage hairline you are asking for at 20, that is a warning sign about the clinic, not a service.
The decision framework
| Your situation | Right next step |
|---|---|
| Just noticed thinning, age 18–22 | Diagnosis and medication — not surgery |
| Actively shedding, visible recession | Medication, blood tests, 12-month documented review |
| On medication 12 months, loss has stopped, still have visible recession | Reassess — surgery may be discussed, conservatively |
| Stable for 2+ years, good donor area, limited defined loss | Reasonable transplant candidate |
| Scar, burn, or eyebrow/beard restoration | Transplant appropriate regardless of age |
| Rapid diffuse thinning all over, including sides and back | Not pattern baldness — needs medical investigation first |
That last row matters. Loss that includes the back and sides, or comes with sudden heavy shedding, is usually not androgenetic alopecia. Telogen effluvium, thyroid disorder, anaemia, or an autoimmune condition can all look alarming and are all treatable — but only after a correct diagnosis. A clinic that sells you a transplant without ruling these out is not assessing you.
What a proper assessment should include
If you consult anywhere and none of these happen, get a second opinion:
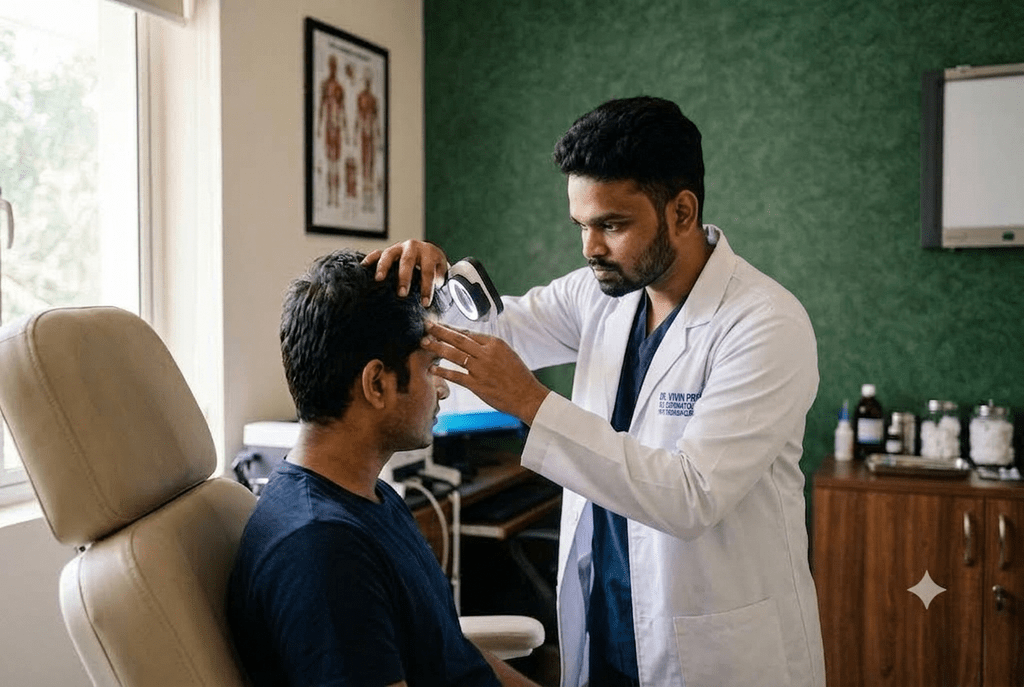
- Examination of the scalp under magnification to measure miniaturisation, not just a look at your hairline
- Assessment of donor density at the back and sides
- Norwood grading with standardised photographs stored for comparison
- Family history on both sides
- Blood tests where diffuse shedding, fatigue, or dietary risk factors are present
- A direct answer to the question “should I have surgery now, and why not”
At Dheeran Hair Transplant Clinic, Dr. Vivin Prasadh (MBBS, MD) has spent over seven years assessing more than 4,000 patients, and a meaningful number of those consultations end with the advice to start medication and come back in a year. That is not a lost sale. That is the correct treatment for that patient at that time.
The cost argument nobody makes
Young patients often compare medication and surgery on price and conclude that surgery is the “one-time” option. Run the numbers properly over a decade and the comparison flips.
Medication is a recurring monthly cost, but modest. A transplant is a significant one-time cost — but a transplant done at 19, without medication to protect the surrounding hair, frequently becomes two or three procedures by 35. Each one costs more than the first, and each one consumes donor hair that cannot be replaced.
The genuinely cheapest long-term path for most men who start losing hair at 18 is: medication early, medication consistently, and surgery once — later, correctly planned, done a single time.
Frequently asked questions
Is 18 too young for a hair transplant? In almost all cases of pattern hair loss, yes. The loss pattern has not stabilised, so the surgeon cannot know how much donor hair to preserve. The exceptions are scar repair, burns, and eyebrow or beard restoration.
Can I stop hair loss at 18 without medicine? No treatment other than medication has been shown to stop androgenetic alopecia. Diet, sleep, stress management and scalp care support overall hair health and prevent additional shedding, but they do not block DHT.
If I start finasteride at 19, do I take it forever? For as long as you want to keep the benefit. Stopping means DHT resumes its effect and the hair you preserved will be lost over the following months. This is one of the main things to discuss with your doctor before starting.
Will a transplant at 20 mean I need another one later? Very likely, unless the underlying loss is controlled with medication and the hairline is designed conservatively. This is the strongest single argument for waiting.
Does stress cause hair loss at this age? Stress causes telogen effluvium — a temporary, diffuse shedding that usually recovers within a few months. It can also accelerate the visible progression of pattern loss that was already beginning. Exam stress is rarely the whole story if your hairline is receding in a pattern.
My father is bald — does that mean I definitely will be? It raises your risk considerably, but inheritance comes from both sides of the family and is not a simple on-off switch. It also does not tell you the speed or the final grade. This is exactly why documented monitoring over 12 months is more useful than family history alone.
Is PRP a replacement for a transplant? No. PRP stimulates existing miniaturising follicles. It cannot create hair where follicles are gone. It is a support treatment, most useful in younger patients with early thinning.
Can I do a transplant during my college holidays? The procedure itself allows a return to normal routine within days, but at 18–22 the timing question is not about your holiday schedule. It is about whether surgery is appropriate at all yet.
What to do this week

If you are between 18 and 22 and your hairline is changing, the most valuable thing you can do is not book a surgery. It is get a proper diagnosis, start the right medical treatment, and create a documented baseline — because the man who starts treatment at 19 and has surgery at 27 ends up with far better hair at 40 than the man who has surgery at 19.
Book a consultation at Dheeran Hair Transplant Clinic
Dr. Vivin Prasadh, MBBS, MD — 7+ years of experience, 4,000+ patients, 98% graft survival rate, non-root touch FUE technique.

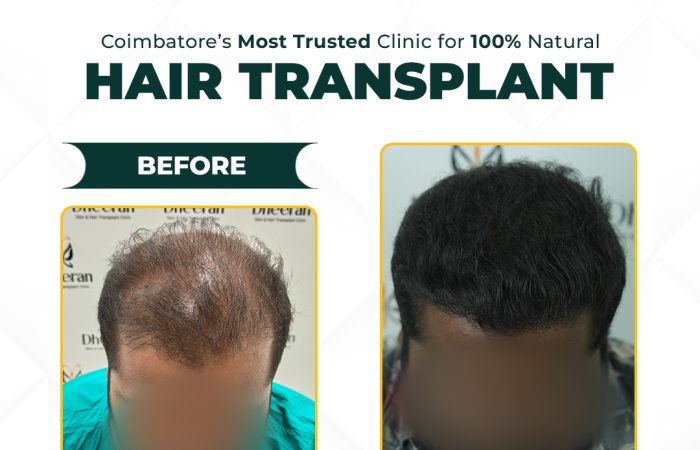
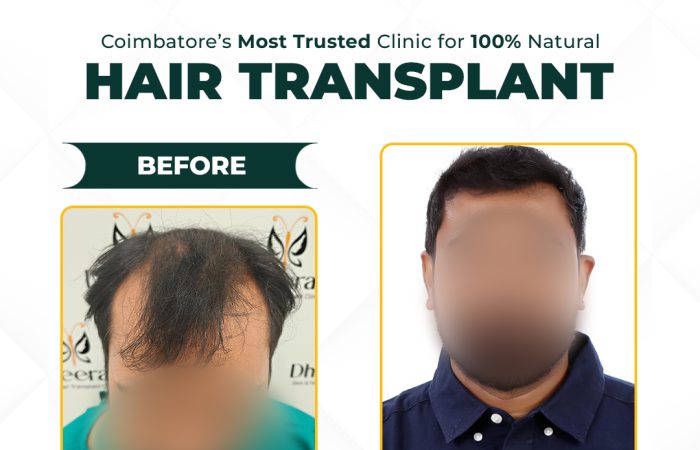
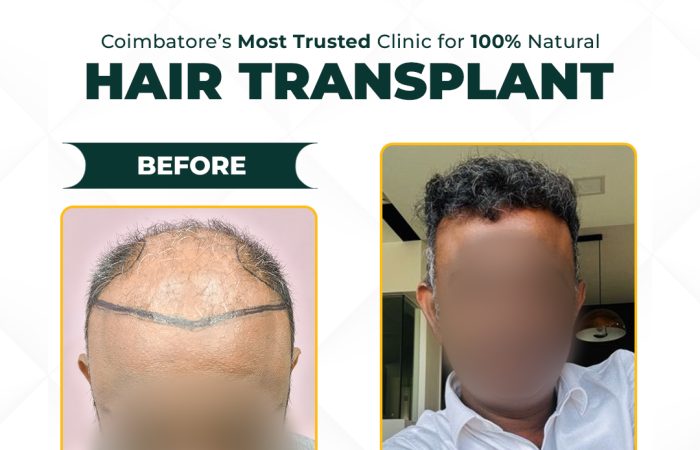
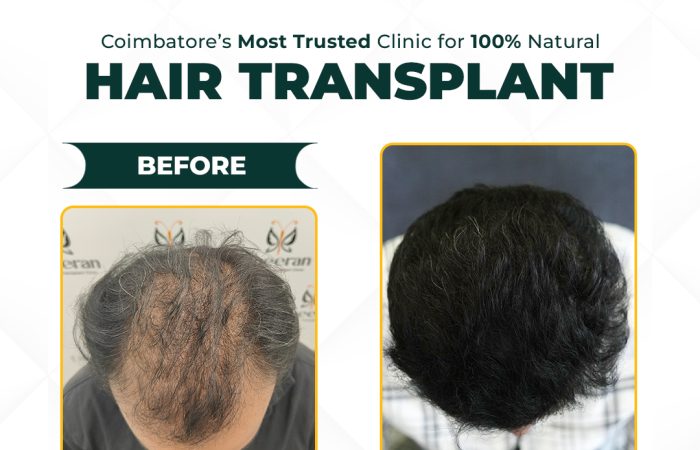
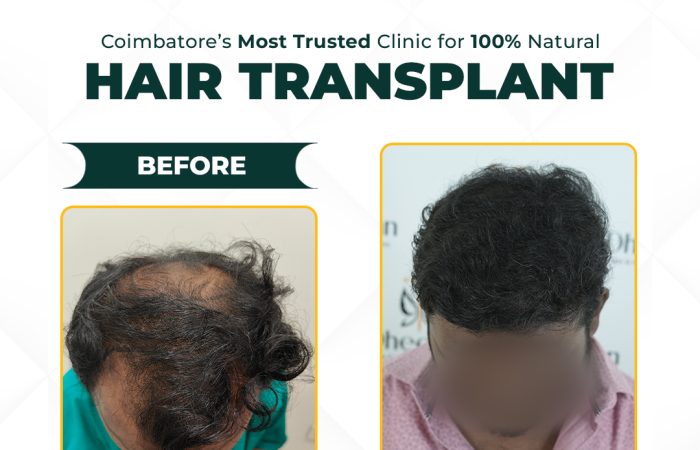
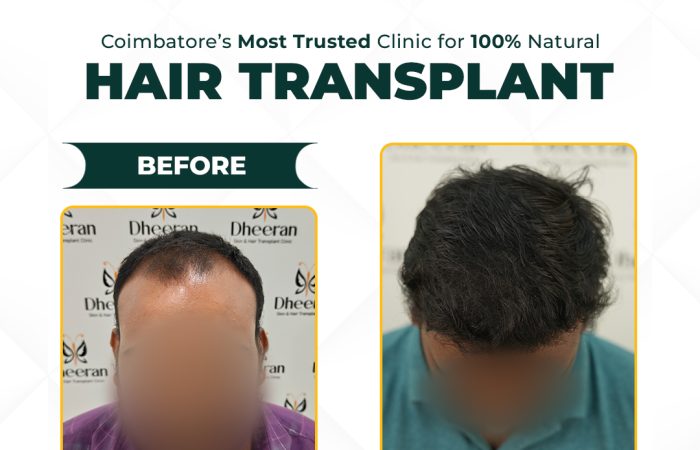


Patient Testimonials & Results
▶ Watch All Videos








 Dr. Vivin Prasadh